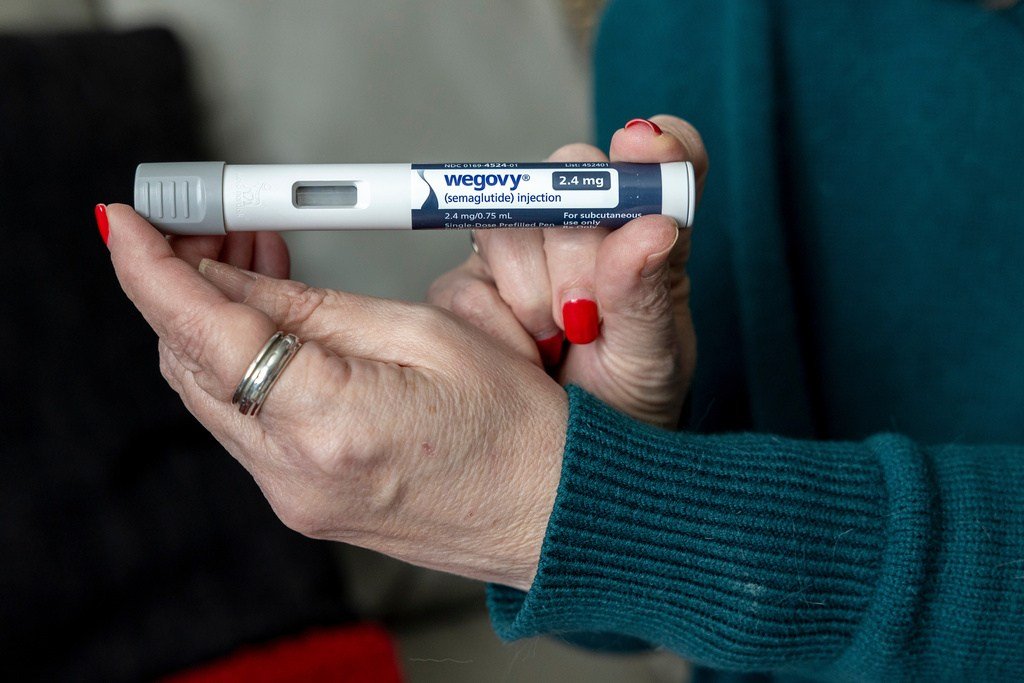
In the two months since the Medicare GLP-1 Bridge program launched on July 1, over 600,000 beneficiaries have enrolled, a sign that the demand for obesity treatment among older Americans has been vastly underestimated. The program, which provides eligible Part D enrollees with access to certain GLP-1 medications for a $50 monthly copay, was designed as a temporary stopgap. But its rapid uptake is prompting advocates to ask: what happens when the bridge ends?
For decades, Medicare has lagged behind in covering obesity treatments, even as the science of obesity as a chronic disease has advanced. The Bridge Program was a first step toward closing that gap, but it is set to expire at the end of next year. The early enrollment figures, which show that most participants had never before had access to these drugs for obesity, underscore the scale of the unmet need.

“Our organization welcomes this progress. It is a bridge,” said Joseph Nadglowski, president and CEO of the Obesity Action Coalition. “But where will that bridge take us?” His comments reflect a broader concern among patient advocates that the program’s temporary nature could leave millions of seniors without affordable treatment once the funding runs out.
Obesity affects roughly 40 percent of American adults, and its prevalence is even higher among older populations. Yet coverage policies have historically treated obesity as a lifestyle issue rather than a chronic disease, a stance that has led to persistent stigma and barriers to care. GLP-1 medications, while not suitable for everyone, have proven effective for many patients, and experts argue that coverage decisions should be made by doctors and patients, not by insurance formularies.
The Bridge Program’s enrollment numbers are a powerful indicator of the demand for these treatments. “This is not simply strong enrollment,” Nadglowski said. “It is evidence of a need that has gone unmet for far too long.” The program’s success, however, raises the stakes for policymakers: if the program is allowed to lapse, it would send a signal that obesity care remains a second-class benefit.
The next 15 months offer a window to demonstrate the value of expanding access to obesity medications. But advocates are already calling on Congress to make the program permanent, or at least to extend it while a more comprehensive solution is developed. The legislative efforts to address Medicare waiting periods show that there is appetite for reform, but broader coverage for obesity drugs remains a tougher sell.
For seniors, the consequences of inaction are real. Without coverage, many will be forced to choose between paying for medications out of pocket or forgoing treatment altogether. That is a choice no one should have to make, especially when effective therapies exist.
The Bridge Program is a step in the right direction, but it is only a temporary fix. As Nadglowski put it, “Every bridge is supposed to take us somewhere. This one should lead to comprehensive, affordable and lasting access to obesity care.” Whether that destination is reached will depend on whether lawmakers act before the program expires.

